
Hypermobility Disorders - A guide to hypermobility, assessment and the Acubody clinical approach
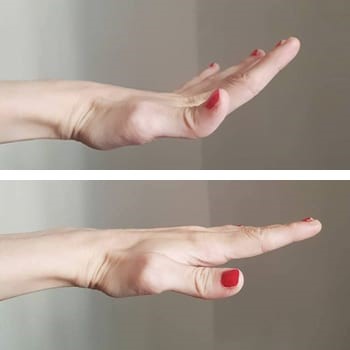
What is Hypermobility?
We are all born with different degrees of flexibility, tissue laxity and neuromuscular characteristics. Genetics plays a significant role in this, alongside the type and amount of physical activity and training we experience, particularly during childhood and adolescence.
Hypermobility describes joints that move beyond the normal range of movement. This is usually associated with increased laxity in the ligaments and joint capsules that provide passive support to our joints.
Some people are naturally very flexible without experiencing any problems and can even be an advantage in some activities. For others, however, hypermobility can be associated with joint instability, recurrent injuries, pain, muscular tension and fatigue.
Hypermobility exists on a spectrum, and can be associated with other disorders of wider systems. It is important to distinguish between simply being naturally flexible and having symptomatic hypermobility that affects physical health and quality of life.
Understanding the terminology: GJH, HSD and hEDS
There have been important changes in the way hypermobility conditions are classified. The 2017 international framework for joint hypermobility and related conditions introduced terminology intended to distinguish between asymptomatic joint hypermobility, symptomatic hypermobility and specific connective tissue disorders.
Previously, people with symptomatic hypermobility were often diagnosed with benign joint hypermobility syndrome (BJHS), also known as joint hypermobility syndrome (JHS). The revised Brighton criteria, published in 2000, combined joint flexibility with symptoms such as chronic pain, recurrent dislocations and soft-tissue injuries. The word benign was used in the label due to the absence of associated organ problems e.g. the ligaments in the heart being affected as can be the case in some hypermobile conditions.
The main terminology now used is:
- Generalised joint hypermobility (GJH): increased joint flexibility affecting multiple areas of the body. This does not necessarily cause symptoms or require treatment.
- Hypermobility spectrum disorder (HSD): symptomatic joint hypermobility associated with problems such as pain, instability, recurrent injuries or functional difficulties, where the person does not meet the criteria for hEDS or another specific connective tissue disorder.
- Hypermobile Ehlers-Danlos syndrome (hEDS): a heritable connective tissue disorder characterised by generalised joint hypermobility and additional systemic and musculoskeletal features which are combined from a variety of areas.
HSD and hEDS are distinct diagnostic categories, but they can share many symptoms and functional difficulties. HSD should not be thought of simply as a mild form of hEDS: people with either condition can experience considerable pain and disability.
The older BJHS diagnosis has not become synonymous with hEDS. Someone diagnosed with BJHS in the past might now meet the criteria for HSD or hEDS, depending on their clinical presentation. The old diagnosis is not automatically converted into either category.
How do you know if you are hypermobile?
One commonly used clinical screening tool is the Beighton score. This assesses flexibility across nine points in the body and is used to help identify generalised joint hypermobility.
The assessment includes:
- Little fingers that bend backwards beyond 90 degrees (one point for each hand).
- Thumbs that can touch the forearm (one point for each hand).
- Elbows that hyperextend beyond 10 degrees (one point for each elbow).
- Knees that hyperextend beyond 10 degrees (one point for each knee).
- Being able to place both palms flat on the floor with the knees straight (one point).
The maximum score is nine. For consistency, joint angles should be assessed using the standardised positions described in the clinical criteria; a goniometer can be used to measure angles.
What is a positive Beighton score?
The internationally recognised adult diagnostic criteria for hEDS use the following age-adjusted thresholds:
Age / developmental stage | Score |
Prepubertal children | 6 or more out of 9 |
Pubertal individuals up to age 50 | 5 or more out of 9 |
Over 50 | 4 or more out of 9 |
These thresholds are used to identify generalised joint hypermobility, not to diagnose hEDS or HSD in isolation. The adult hEDS criteria use a threshold of at least 5/9 up to age 50 and 4/9 over age 50; the paediatric framework uses 6/9 for children from age five to biological maturity.
A useful clinical reference for the scoring method and age-related thresholds is GeneReviews: Hypermobile Ehlers-Danlos Syndrome.
The Five-Point Questionnaire
The Five-Point Questionnaire (5PQ) can help identify historical hypermobility in people who may have lost some flexibility through ageing, injury or other changes. The questionnaire is described in GeneReviews and is included in the 2017 hEDS assessment framework.
The questions ask whether you:
- Can now, or could previously, place your hands flat on the floor without bending your knees?
- Can now, or could previously, bend your thumb to touch your forearm?
- As a child, could contort your body into unusual shapes or perform the splits?
- As a child or teenager, experienced repeated shoulder or kneecap dislocations?
- Consider yourself double-jointed?
Two or more positive answers indicate a positive questionnaire. Under the adult hEDS criteria, this can help establish generalised joint hypermobility when someone scores just one point below the relevant Beighton threshold. It is not a stand-alone diagnostic test.
Limitations of the Beighton score
Although clinically useful as an overview, the Beighton score has important limitations. It assesses only a small selection of joints and does not include areas such as the shoulders, hips, ankles and feet. It also tells us nothing about joint stability, proprioception, muscular control or whether someone experiences pain.
Consequently, someone can have significant symptomatic hypermobility and be symptomatic without achieving the required Beighton score. A proper assessment needs to consider medical history, previous flexibility, recurrent injuries, joint instability and other symptoms alongside the physical examination.
For adults, hEDS has additional diagnostic requirements beyond generalised joint hypermobility. These include particular connective tissue features, family history and musculoskeletal complications, together with the exclusion of alternative diagnoses. There is currently no genetic or laboratory test that confirms hEDS.
The 2017 international classification of the Ehlers-Danlos syndromes sets out the adult hEDS criteria. Children and adolescents who have not reached biological maturity are assessed using a separate paediatric framework introduced in 2023, which recognises that some features used to diagnose adult hEDS develop over time. See Tofts et al. (2023), Paediatric joint hypermobility: a diagnostic framework and narrative review.
Ultimately, the Beighton score is a screening component, not a diagnosis in itself.

Why can hypermobility cause pain and instability?
An important part of understanding hypermobility is proprioception: your body’s ability to sense where your joints and limbs are in space.
Ligaments and fascia contain specialised nerve endings called mechanoreceptors, which contribute to our sense of joint position and movement. When ligaments are particularly lax, this sensory feedback may be less reliable. This can make it harder for the nervous system to regulate movement and maintain stability, particularly towards the extremes of your range of motion.
As a result, you may have considerable flexibility but feel insecure or weak in certain positions. You can even experience this as feeling stiff even though when you have a greater than normal range of movement. For example, hanging from a bar, supporting your weight through your arms or controlling a deep squat might feel uncomfortable or unstable.
The nervous system can respond to this perceived lack of stability by increasing muscular tension. Muscles effectively brace to protect the joints, sometimes becoming persistently tight, sore and less effective at producing movement.
This can create a frustrating cycle:
- Joint laxity makes it harder to maintain stability.
- Muscles compensate by tightening and guarding.
- Persistent tension contributes to pain and fatigue.
- Pain and reduced muscular output make movement and exercise more difficult.
- Reduced strength and control can contribute to further instability, injury and fatigue.
When Hypermobility is a More Serious Concern
This also explains why hypermobile people can experience both excessive flexibility and significant stiffness. You may be extremely mobile in some joints while feeling restricted and tight elsewhere.
In clinical practice, we often see people with a combination of recurring injuries, muscular guarding and persistent pain who have never previously considered hypermobility as a contributing factor. It is often important to learn how to release that tension in order to be able to strengthen and stabilise effectively without pain.
Why strength and control matter more than flexibility
One of the biggest misconceptions about hypermobility is that having a large range of movement means having good mobility.
In reality, flexibility and functional mobility are quite different. Having access to a large range of movement does not necessarily mean you have the strength or control to use it safely.
For example, you might be able to squat all the way down with ease, but struggle to control the movement when rising just an inch or two. Strength and coordination need to be developed throughout your available range of motion, not simply at the extremes.
For most people with symptomatic hypermobility, developing muscular strength, joint control and proprioception is the foundation of effective management. The NHS identifies strength and fitness training as central to managing symptomatic joint hypermobility. Exercise should be appropriately graded and progressed, with particular attention to controlling movement rather than simply building strength as it can lead to pain and injury in sensitised individuals.
We recommend avoiding habitual joint locking, excessive end-range stretching and exercises that repeatedly load unstable positions without adequate muscular control. In an activity where you need to have straight limbs, eg dance or some yoga postures, it’s better to think about ‘stacking’ and ‘lengthening’ to keep your alignment without locking or hyperextending.
Stretching is not necessarily prohibited, but it should not be the priority. Where appropriate, it should focus on muscle tissue rather than placing strain on already lax ligaments and joint capsules. Techniques like keeping a slight bend in the joints and using intent through the hands and feet can help in this while also building proprioception.
How can acupuncture and hands-on treatment help?
Acupuncture cannot change the underlying laxity of your ligaments or reverse hypermobility. However, it may have a useful supporting role in managing associated pain and muscular tension, and in autonomic nervous system regulation.
People with hypermobility often develop persistent areas of muscle guarding, trigger points and soft tissue sensitivity. Acupuncture and gentle soft tissue release techniques may help reduce discomfort and muscular tension, making it easier to move and participate in rehabilitation.
It is important to be clear about the evidence. There are currently no clinical trials specifically testing acupuncture for hEDS or HSD. However, there is a wider body of research supporting acupuncture for certain types of chronic pain.
NICE guidance on chronic primary pain recommends considering a single course of acupuncture, within specified conditions, as one option for adults. This guidance is about chronic primary pain generally; it is not a recommendation specifically for hypermobility. See NICE guideline NG193, recommendation 1.2.5.
We therefore use acupuncture selectively, with realistic expectations and an emphasis on meaningful improvements in pain and function.
Hands-on treatment is also not an end in itself. Our aim is to help reduce pain and guarding, improve movement and create an opportunity for you to develop better muscular control. The next step is to use movement and exercise to help establish those improvements over time.
Some patients also experience flare ups after strong treatment, especially if they also have fibromyalgia (studies show 45-64% of people with fibromyalgia are also hypermobile so there’s a big overlap). This can be a particular risk with myofascial and trigger point therapy, so they must be sensitively applied.

Hypermobility treatment and the nervous system
Ultimately the pain and tension are mediated by the nervous system. Fibromyalgia does and hypermobility syndromes can involve a neurological phenomenon called central sensitisation. Over long periods of time persistent pain signals cause the nervous system itself to become sensitised, so discomfort can be amplified and pain reported though there is no longer any tissue damage. This mechanism also relates to chronic pain.
It is hypothesised that one of the ways acupuncture is useful in treating chronic pain is that is interrupts these signals and allow the nervous system to start recalibrating, and desensitising. Manual neuromuscular techniques also employ the stimulation of specialised mechanoreceptors to trigger reflex effects that essentially start showing the nervous system how to tolerate load again.
Applying pressure to these areas while combining it with active or passive movement provides sensory input alongside changes in muscle length and tension.
This combined stimulation may influence neuromuscular regulation, helping to modify excessive muscle tone and protective guarding. The result can be improved movement, more comfortable muscle lengthening and better coordination between muscles.
This approach is informed by our understanding of proprioception and the nervous system’s role in regulating muscle activity. It provides a useful way of preparing the body for subsequent movement retraining and progressive strengthening (Schleip R. 2003)
If the nervous system isn’t ready to process a change in tension and therefore maybe stability it can cause spasm and increase in pain and tension later. For this reason it is important your practitioner understands your situation and proceeds gently and gradually paying attention to how your body responds.
And this is why following up with conscious movement training is really important to progress these changes and hold onto them, build strength and release bracing. That is also working with the nervous system.
Our clinical approach to managing hypermobility
At Acubody, we take an individualised approach to hypermobility, recognising that no two people present in quite the same way.
We regularly work with people who have a history of recurring injuries, persistent pain and complex musculoskeletal problems. Hypermobility is often an important underlying factor that has previously gone unrecognised.
Our approach combines three complementary elements.
- Acupuncture and soft tissue treatment
We use acupuncture, trigger point release and gentle to moderate soft tissue techniques to help manage pain, reduce muscular guarding and improve comfort and freedom of movement. The focus is on reassuring the nervous system so it can start to tolerate load more effectively.
We adapt treatment to your particular presentation, taking account of tissue sensitivity, easy bruising and any associated medical conditions. We avoid forceful manipulations, aggressive stretching or traction.
The aim is to help calm sensitive tissues and reduce excessive muscular tension, creating an opportunity for more comfortable and controlled movement on which to build strength so the patient can recover their agency. In the log term teaching patients how to manage their conditions, empowering you is the best strategy.
- Neuromuscular rehabilitation and movement training
We use the Go-To system, developed by sports physiotherapist Dave O’Sullivan, as one of our starting points for rehabilitation. The system is really powerful in identifying what is and isn’t doing its job in a pattern of dysfunction.
This approach combines assessment, soft tissue release of specific active points, muscle energy techniques and progressive exercise. Rather than simply treating an isolated painful joint, we look at how different parts of the body work together.
This is particularly important with hypermobility, where instability and compensation in one area can affect movement throughout the body. Simply stabilising one joint at a time may not address the wider movement patterns contributing to your symptoms.
Exercise begins with accessible, comfortable movements and gradually progresses as your strength, coordination and confidence improve.
- Pilates, qigong and strength development
We use a combination of Pilates, qigong and functional strength training to develop stability, proprioception and control.
Individual Pilates sessions can be particularly useful because exercises can be adapted to your capabilities. Studio equipment provides adjustable resistance, supported positions and useful feedback, allowing you to develop strength without unnecessarily challenging unstable joints.
Qigong offers another way to develop body awareness and movement control. Its slower, coordinated movements can help you explore movement without excessive muscular tension, while gradually building strength and coordination.
We also draw on bodyweight strength training and the praxis/ GMB method to develop practical strength, mobility and movement skills. The emphasis is on building strength and control throughout your available range. There is an element of flexibility training in the system, but it is always balanced with control. The method prioritises body awareness, and encourages you to start from where you are and progress at your own pace rather than trying to hit arbitrary traing metrics.
Training Around Hypermobility
Having hypermobile joints does not mean you need to avoid exercise or restrict what you do. In fact, developing strength and control can help you make much better use of your natural mobility.
The key is learning to work with your body rather than continually pushing towards the limits of your flexibility.
- Developing strength throughout your available range of movement.
- Learning to control joints rather than habitually locking them out.
- Building stability through coordinated muscular activity.
- Progressing exercise gradually, according to your individual capabilities.
- Recognising when muscular tension is protective and learning to release unnecessary guarding.
As your strength and control develop, your training can become increasingly specific to your goals. You can improve your proprioception and body awareness with practise and training.
Perhaps you want to return to running, play golf without recurring back pain, attend exercise classes with friends or develop the strength to perform a handstand without wrist pain. Rehabilitation can be shaped around these goals.
Hypermobility does not have to define what you can and cannot do. With the right approach, it is often possible to improve your physical capabilities considerably.
Living well with hypermobility
Hypermobility can sometimes be associated with wider symptoms, including fatigue, dizziness, easy bruising and problems affecting the autonomic nervous system. Conditions such as postural orthostatic tachycardia syndrome (POTS), dysautonomia, fibromyalgia and mast cell activation syndrome can also occur alongside certain hypermobility conditions.
If you experience significant or unexplained symptoms, recurrent dislocations or suspect you may have hEDS or HSD, appropriate medical assessment is important. Our treatment is focused primarily on the musculoskeletal aspects of hypermobility and can form part of a wider management plan.
A personal and experienced approach
Duncan McGechie has a particular interest in hypermobility, having experienced it himself. His own diagnosis of benign joint hypermobility syndrome (BJHS) in 1999 gave him a personal insight into some of the challenges associated with the condition and a motivation to find the best ways of managing it.
This, combined with more than 23 years of clinical experience in acupuncture, Chinese medicine and musculoskeletal treatment, informs our approach to helping people manage hypermobility.
We recognise that simply treating pain or releasing tight muscles is rarely enough when underlying joint instability and movement patterns remain unchanged.
Our aim is to help you understand your body, reduce unnecessary pain and tension, and develop the strength, stability and confidence to move well.
Most importantly, we want to help you get back to doing the things you enjoy, whether that is exercise, sport, work or simply moving through everyday life with greater comfort and confidence.
Acubody Therapies – London
Duncan sees patients at London Natural in Holborn and the Acubody Therapies studio in Grove Park, Lewisham.
Duncan McGechie (BA, MSc, Grad Dip, MBAcC, MBMAS, MRCHM, MISRM, FHEA) has practised acupuncture and Chinese medicine since 2003 and myofascial release and neuromuscular therapy since 2006. He is a member of the British Acupuncture Council, the British Medical Acupuncture Society, the Register of Chinese Herbal Medicine and the Institute of Sports and Remedial Massage.
Read Duncan’s full profile.
References and further reading
The following sources are linked from the relevant sections of the article. They provide the principal classification, diagnostic and guidance references used in this draft.
- Grahame R, Bird HA, Child A (2000). The revised (Brighton 1998) criteria for the diagnosis of benign joint hypermobility syndrome (BJHS). Journal of Rheumatology, 27(7), 1777–1779. View source
- Castori M et al. (2017). A framework for the classification of joint hypermobility and related conditions. American Journal of Medical Genetics Part C, 175(1), 148–157. View source
- Malfait F et al. (2017). The 2017 international classification of the Ehlers-Danlos syndromes. American Journal of Medical Genetics Part C, 175(1), 8–26. View source
- Hypermobile Ehlers-Danlos Syndrome. NCBI Bookshelf. View source
- Tofts LJ et al. (2023). Pediatric joint hypermobility: a diagnostic framework and narrative review. Orphanet Journal of Rare Diseases, 18, 104. View source
- The Ehlers-Danlos Society. Assessing Joint Hypermobility: The Beighton Scoring System. View source
- The Ehlers-Danlos Society. hEDS Diagnostic Checklist. View source
- NICE guideline NG193. Chronic pain (primary and secondary) in over 16s: assessment and management. Recommendation 1.2.5: acupuncture for chronic primary pain. View source
Editorial note: This is an editable working draft. Clinical claims and local service details should be checked before publication, particularly where the article describes treatment scope, contraindications or diagnostic criteria.






